Tear duct obstruction occurs when the ducts carrying tears from the eye to the nasal cavity become narrowed or blocked. In this condition, tears flow outward, causing watering, discharge, and frequent infections.
In adults, it generally develops because of inflammation, aging, or trauma. Congenital narrowing of the duct is common in babies. The symptoms often negatively affect quality of life.
Dye tests, endoscopic examinations, and imaging methods may be used to evaluate the tear ducts. Early diagnosis may allow the use of simpler treatment options.
Treatment options include massage, probing procedures, and surgical interventions. Surgery is the most effective solution for permanent obstructions. Regular follow-up is necessary to prevent infections.
| Definition | Blockage or narrowing of the ducts that carry tears from the eye to the nose. It causes persistent watering or eye infections. |
|---|---|
| Causes |
- Congenital: Incomplete development of the tear ducts.
- Aging: Narrowing of the ducts.
- Trauma: Injuries to the face or nose.
- Infections: Chronic sinusitis or conjunctivitis.
- Tumors: Rare conditions that block the duct.
| Symptoms |
|---|
- Persistent watery eyes.
- Redness and swelling around the eye.
- White or yellowish discharge from the tear duct.
- Recurrent eye infections.
| Diagnostic Methods |
|---|
- Physical examination.
- Tear duct dye test to evaluate tear drainage.
- Probing of the tear duct.
- Imaging methods such as dacryoscintigraphy and CT.
| Treatment Methods |
|---|
- Congenital Obstruction: Treatment with massage and eye drops. Most cases open spontaneously.
- Infection: Antibiotic eye drops.
- Probing or Dilation: Used to open the obstructed duct.
- Surgery (Dacryocystorhinostomy): Creation of a new passage to restore tear drainage.
- Stent Placement: Used to keep the duct open.
| Complications |
|---|
- Chronic eye infections.
- Abscesses around the eye.
- Vision problems.
| Prevention Methods |
|---|
- Maintaining proper eye hygiene.
- Treating eye infections early.
- Protecting the face and eyes from trauma.
| Risk Factors |
|---|
- Advanced age.
- Chronic sinusitis or nasal infections.
- Congenital tear duct abnormalities.
- Previous facial surgery.
Tear duct obstruction is the blockage of the nasolacrimal duct, which carries tears into the nasal cavity. This obstruction may cause persistent watery eyes, discharge, and infection. It may be congenital or develop later. Depending on its cause and severity, treatment may involve medication, massage, or surgery known as dacryocystorhinostomy.
Tear duct obstruction may occur in any age group, but the most prominent causes differ between age groups. For example:
- Newborns and Babies
In babies, a thin membrane at the lower end of the duct, known as the valve of Hasner, often fails to open after birth. When this membrane remains closed, tears cannot drain toward the nose, causing persistent watering and discharge. In babies, this condition frequently resolves spontaneously within the first few months.
- Adults
The most common causes in adults include infections, chronic nasal or sinus problems, traumatic fractures, tumors, and age-related anatomical changes. Although rare, tumors located next to the lateral wall of the nose may press against the tear duct as they grow and obstruct tear drainage.
- Older Adults
With advancing age, degenerative changes may occur in the walls of the tear ducts and surrounding tissues. The ducts may become narrow and sometimes close completely. Sagging or anatomical abnormalities of the eyelids, such as ectropion or entropion, are also more common in older adults. These eyelid abnormalities may interfere with tear drainage.
- People With a History of Surgery or Trauma
Adhesions may develop within the tear duct following nasal surgery, facial trauma, or sinus surgery. Just as soil that falls onto the side of a road may form a barrier and block water flow after repeated rainfall, scar tissue that develops after surgery or trauma may obstruct normal drainage through the duct.
Tear duct obstruction is therefore a multifactorial problem that cannot be attributed to a single age group or cause. Considering each factor helps us understand the importance of accurate diagnosis and appropriate treatment.
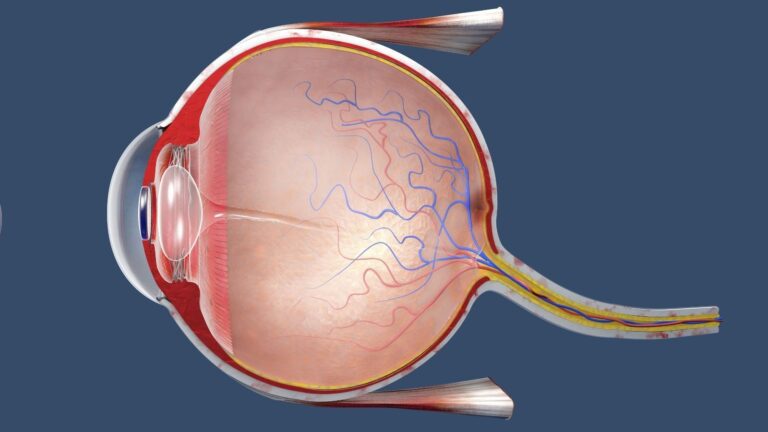
The most common analogy used to explain this condition is a system of pipes carrying water. Tears that moisturize the eye are produced by the lacrimal gland, which is located in the outer portion of the upper eyelid. After spreading across the ocular surface, the fluid enters small openings called puncta at the inner corner of the eye, on the nasal sides of the upper and lower eyelids. It then passes through the canaliculi. The canaliculi join and lead into the lacrimal sac, which empties into the nasal cavity through the nasolacrimal duct.
When an obstruction develops at any point, it is similar to closing the end of a hose through which water should flow. Tears accumulate backward, causing excessive watering on the ocular surface, followed by discharge and crusting. The obstruction may result from failure of a membrane to open, as seen in babies, inflammation within the duct, bony projections caused by trauma, or pressure from surrounding tissues.
When the opening of the duct narrows for any reason, tears collect in the area. This pooling creates an ideal environment for microorganisms to multiply, leading to frequently recurring infections. The situation can be compared to how the water in an aquarium quickly becomes dirty when its filtration system stops working. Similarly, impaired tear duct function disrupts the natural cleansing of the eyes.
This condition most commonly presents with watery eyes. In some people, the symptoms are mild, while in others they may lead to much more serious findings.
- Persistent or Recurrent Watery Eyes (Epiphora)
Instead of draining toward the nose, tears flow outward and down the cheeks. Watering becomes particularly noticeable in windy, cold, or dusty environments and in situations involving sensitivity to bright light.
- Eye Discharge and Mucopurulent Secretion
When an obstruction is present, the lacrimal sac cannot empty completely. The fluid accumulating in the sac becomes a breeding ground for bacteria. Yellow-green pus may eventually develop, causing discharge that makes the eyelids stick together in the morning.
- Redness and Tenderness Around the Eye
Pain or tenderness may be felt, particularly when pressure is applied near the inner corner of the eye. This area may appear swollen and red. The condition may indicate inflammation of the lacrimal sac, known as dacryocystitis.
- Blurred Vision
Excessive watering creates a continuous layer of fluid on the ocular surface and may interfere with clear vision. This is similar to trying to see clearly through a fogged window.
- Recurrent Infections
Tear duct obstruction is not only a mechanical problem. It also creates conditions in which infections may become chronic. Some patients may experience repeatedly recurring redness and inflammation of the eye.
- Fever and Deterioration of General Health in Rare Cases
If the infection spreads beyond the lacrimal sac into the surrounding tissues, it may cause periorbital cellulitis or, at a more advanced stage, orbital cellulitis. Systemic symptoms such as fever, weakness, and pronounced swelling around the eye may occur. This is an urgent condition.
Although tear duct obstruction may affect people of any age or sex, certain risk groups can be identified:
Newborns
During fetal development, a thin membrane may remain at the lower end of the nasolacrimal duct. This membrane normally ruptures and opens at birth or during the first few months. If it fails to open, an obstruction develops. This is the most common cause of watery eyes in babies.
- Advanced Age
As a person ages, the tissues around the tear duct may lose elasticity and structural support. The likelihood of chronic inflammation and fibrosis, or scar tissue formation, also increases. These changes may contribute to obstruction.
- Women
Some studies have found that tear duct obstruction may occur more frequently in women. This may be because women tend to have anatomically narrower tear ducts. Hormonal factors may also have an effect.
- People With a History of Facial Trauma or Surgery
Fractures involving the nose or orbit, cosmetic nasal surgery, and sinus surgery may damage the tear duct. Sometimes even a small bony projection or thin layer of scar tissue may cause an obstruction.
- People With Nasal Conditions Such as Chronic Sinusitis or Allergic Rhinitis
Because the tear duct is anatomically close to the nasal and sinus passages, persistent inflammation or an anatomical abnormality within the nose may also adversely affect tear duct function.
- Tumors or Systemic Diseases
Although rare, tumors that place pressure on the tear duct and systemic inflammatory diseases such as sarcoidosis or Wegener's granulomatosis, now also known as granulomatosis with polyangiitis, may increase the risk of tear duct obstruction.
Watery eyes may initially appear to be a simple complaint, but the condition can progress to more serious problems if left untreated:
- Chronic Conjunctivitis
Tears that continuously accumulate in the eye provide a suitable environment for microorganisms to multiply. Recurrent or long-lasting conjunctivitis, which is inflammation of the ocular surface, may cause considerable discomfort.
- Dacryocystitis (Inflammation of the Lacrimal Sac)
The obstruction is generally located below the lacrimal sac or within the duct. When the duct cannot open fully, the lacrimal sac fills and overflows. The fluid inside becomes infected, causing swelling, redness, and pain in the sac. If left untreated, it may cause an abscess or spread to surrounding tissues, resulting in periorbital or orbital cellulitis.
- Eyelid Problems
Persistent accumulation along the ciliary eyelid margin and excessive watering may cause skin irritation and even eczema-like conditions around the eyelid. Laxity of the lower eyelid, known as ectropion, or inward turning of the eyelid, known as entropion, may also create chronic problems.
- Risk of Vision Loss
If an infection spreads to the cornea, it may cause severe wounds and permanent damage to vision. A corneal ulcer is a critical condition that may result in vision loss if treatment is delayed.
- Social and Psychological Effects
Persistent watering, discharge, and crusting may adversely affect daily life. Discomfort such as embarrassment in social settings, difficulty concentrating while working, and the constant need to use tissues may accompany the condition.
The following methods may be used when tear duct obstruction is suspected:
- Comprehensive Eye Examination
The first step is to obtain a detailed patient history and examine the general condition of the eye. Eyelid position, lesions on the ocular surface, discharge, and signs of dacryocystitis are evaluated.
- Fluorescein Dye Test (Dye Disappearance Test)
Fluorescein dye is placed on the ocular surface. Under normal conditions, the dye should disappear into the nose within several minutes. Delayed or absent disappearance suggests a problem with tear drainage.
- Lacrimal System Irrigation and Probing
The doctor enters through the punctum with a special cannula and flushes the system with saline solution. If the patient feels the fluid reaching the throat or nose, the ducts are understood to be open. If the fluid flows outward or refluxes, an obstruction is present. During probing, a thin metal instrument is passed through the duct to identify the location of the blockage. In babies, this procedure is performed for both diagnostic and therapeutic purposes.
- Dacryocystography (DCG)
This is an X-ray-based imaging method in which contrast material is introduced into the duct to examine its structure and the location of the obstruction. It may be preferred when detailed anatomical visualization is required.
- Dacryoscintigraphy
Using a nuclear medicine method, a radioactive substance is placed in the tear drainage system, and its flow is monitored with a gamma camera. This provides a functional assessment of how much of the duct is open or obstructed.
- Endoscopic Examination
The point where the duct opens into the nasal cavity, known as the meatus, is evaluated from inside the nose. During this endoscopy, generally performed by an ear, nose, and throat specialist, polyps, a deviated septum, or other masses narrowing the duct opening may also be detected.
- Computed Tomography (CT) or Magnetic Resonance Imaging (MRI)
CT or MRI may be used if trauma, a tumor, or severe bony deformity is suspected. These methods provide detailed images of bones and soft tissues and may assist with surgical planning.
Different treatment approaches have been developed according to the severity and duration of the obstruction, the patient's age group, and the underlying cause. The shared objective of all treatments is to restore healthy drainage of tears toward the nose.
Conservative (Nonsurgical) Approaches
- Observation and Massage, Particularly in Babies
If the valve has not opened in a baby, the likelihood of spontaneous opening during the first 6-12 months is high. A method known as Crigler massage may be used to apply gentle pressure over the lacrimal sac and help rupture the membrane. This technique, which is demonstrated to families, can be compared to gently pressing on a minor blockage in a hose to open it.
- Antibiotic Drops or Ointments
If infection or discharge accompanies the obstruction, antibiotic eye drops or ointments may be prescribed to reduce the bacterial load. These medications cannot open the obstruction on their own. They only suppress the secondary infection.
- Warm Compresses and Eye Hygiene
Warm compresses applied several times during the day increase circulation around the eye and soften secretions in the obstructed area. Hygiene around the eyes also reduces discharge and bacterial growth.
- Tear Duct Probing, an Interventional Procedure That Is Not Considered Surgery
In babies whose condition does not improve with massage or whose ducts remain closed beyond a certain age, a thin metal instrument is passed through the duct under brief sedation to open the membrane. The success rate of this procedure is very high in babies. It may also be attempted in adults, but success rates vary because the underlying causes are different.
- Balloon Dilation
Balloon dilation may be used in addition to probing. A thin catheter is placed inside the duct, and the balloon at its tip is inflated to widen the narrowed area as it passes through. This method may be considered an intermediate step before surgery.
- Silicone Tube Placement (Intubation)
In some resistant cases, silicone tubes are placed to bypass the obstruction or keep the narrowed area open. The tube remains inside the duct for several months and is then removed. This method encourages the duct to remain permanently open.
Surgical Methods
- Dacryocystorhinostomy (DSR or DCR)
This is the most commonly performed surgical procedure. A new passage or opening is created between the lacrimal sac and the nasal cavity. This bypasses the portion below the obstruction and allows tears to drain into the nose. The procedure may be performed externally through a skin incision or endoscopically through the nose. The endoscopic method does not leave a visible scar and involves less intervention in the nasal anatomy. The success rate is high and may exceed 90%.
- Laser DCR
Laser DCR is based on the same principle as conventional DCR, but the opening in the bone is created using a laser. Its advantages include a shorter operation and less bleeding. However, it may not be suitable for every case. In certain situations, its success rate may be lower than that of conventional DCR.
- Dacryocystectomy
This procedure involves completely removing the lacrimal sac. It is generally preferred in very elderly patients or when recurrent severe infections have permanently damaged the sac. This method does not create a new route to maintain tear drainage. Its purpose is only to eliminate the sac as a source of infection and pain.
- Surgical Resection if a Tumor Is Present
If a tumor is causing the obstruction, surgical removal of the tumor or additional treatments such as radiotherapy or chemotherapy may be required. An intervention to open the tear duct is then planned either at the same time as the oncological treatment or afterward.
Each of these treatment options is evaluated according to the patient's age, the level of the obstruction, and accompanying conditions such as infection, a tumor, or a history of trauma. Minimally invasive methods may be sufficient for some patients, while others may require immediate surgery.
Surgical intervention is generally considered in the following situations:
- Failure of Conservative Methods
Surgery may be required if massage and probing in babies or treatments such as antibiotics, warm compresses, and probing in adults do not resolve the problem or if the obstruction recurs.
- Severe and Recurrent Dacryocystitis
If inflammation of the lacrimal sac frequently recurs and reduces the patient's quality of life, surgery such as DCR becomes necessary to provide a permanent solution.
- Suspected Tumor or Traumatic Damage
If a mass or fractured bone fragment is blocking the duct, the condition must be corrected surgically and the tumor removed when possible. These factors cannot be eliminated using nonsurgical methods.
- Advanced Age-Related Duct Deformities
In very elderly patients, collapse of the duct or severe changes in nasal anatomy may not improve without surgery.
When making a surgical decision, factors such as the patient's general health, suitability for anesthesia, and ability to receive postoperative care should also be considered.
Untreated tear duct obstruction may cause several problems:
- Chronic Eye Infections and Inflammation
Fluid accumulating within the lacrimal sac becomes contaminated with microorganisms, causing more frequent attacks of dacryocystitis.
- Skin Irritation and Eczema
Constant tear flow keeps the area around the eye wet and irritated. Eczema-like skin lesions may develop over time.
- Abscess, Cellulitis, and Spread Into the Orbit
In some cases, inflammation may spread to neighboring tissues, causing severe swelling, redness, and pain around the eye. If it progresses further, it may cause a serious, life-threatening infection that can spread to the membranes surrounding the brain, such as orbital cellulitis or meningitis.
- Permanent Visual Damage
Chronic infections and ulceration affecting the cornea may cause irreversible vision loss.
Although these complications are relatively rare, they emphasize why patients should take tear duct obstruction seriously.
Although there is no definitive way to prevent the condition completely, some protective measures include:
- Maintaining Eye and Facial Hygiene
Keeping the area around the eyes clean, using personal makeup products, and replacing these products regularly reduce the accumulation of microorganisms.
- Treating Chronic Nasal and Sinus Conditions
Frequently recurring sinusitis and allergic rhinitis may affect the tear duct through swelling and anatomical changes inside the nose. Controlling these conditions reduces the risk of tear duct obstruction.
- Avoiding Trauma
Taking precautions to protect the nose and eye area, such as wearing helmets and protective glasses during sports, may prevent trauma-related bone fractures and subsequent damage to the tear ducts.
- Early Intervention
Recognizing watery eyes in babies at an early stage and applying simple methods such as massage may prevent the problem from progressing. In adults, taking symptoms such as watery eyes and discharge seriously provides an opportunity for early diagnosis and treatment.
- Healthy Nutrition and Supporting the Immune System
A strong immune system is important for reducing susceptibility to chronic infections. A balanced diet, sufficient sleep, and regular exercise positively affect both general health and eye health.
Tear duct obstruction is generally evaluated by ophthalmologists. However, ear, nose, and throat specialists may also become involved if a nasal or sinus-related problem is present or if intervention inside the nose is required during surgery. For example:
- Diagnosis and Initial Evaluation: Generally performed by an ophthalmologist.
- Endoscopic DCR: May require the endoscopic skills of an ear, nose, and throat specialist.
- Suspected Tumor or Systemic Disease: May require a multidisciplinary approach involving specialties such as oncology or rheumatology.
Working with more than one specialist may therefore provide the best outcome in some cases of tear duct obstruction.
In many cases, particularly in babies, tear duct obstruction resolves spontaneously or with simple massage techniques. Early intervention and regular follow-up during infancy therefore generally provide a favorable prognosis. In adults, success rates are usually high when the underlying cause is eliminated, such as through treatment of an infection, removal of an obstructing mass, or correction of an anatomical abnormality.
Surgical interventions, particularly dacryocystorhinostomy, have been performed for many years and have a high success rate. Patients may report a significant reduction or complete resolution of watery eyes. However, surgical success is also affected by factors such as the patient's anatomical characteristics, tissue healing, and the presence of other eyelid problems.
An ophthalmologist should be consulted without delay in the following situations:
- Persistent or Frequently Recurring Watery Eyes
Minor watering may normally occur during seasonal changes or in dusty environments. However, discharge that continues for days or weeks and requires constant wiping should not be neglected.
- Recurrent Eye Infections and Discharge
Professional evaluation is required if the discharge is severe enough to make the eyelids stick together in the morning or if redness and tenderness frequently occur along the eyelid margins.
- Severe Pain, Swelling, and Redness
Pronounced swelling near the inner corner of the eye accompanied by severe pain when pressure is applied may indicate dacryocystitis or an abscess. Early intervention helps prevent serious complications.
- Noticeable Reduction in Visual Quality
A doctor should be consulted promptly if excessive watering or an accompanying corneal condition reduces vision.
- Watering That Does Not Resolve During a Newborn's First 6-12 Months
Although waiting until the age of one is often reasonable for tear duct obstruction in newborns, correct timing of probing is important in persistent cases.
Tear duct obstruction is a universal problem, and similar treatment protocols are used in different parts of the world. For example:
- In the United States, Mayo Clinic protocols encourage massage and eye hygiene during a baby's first year. If these measures are unsuccessful, probing is performed under sedation. Endoscopic DCR is commonly preferred in adults.
- In Europe, some centers commonly use laser DCR, which shortens the length of hospital stay.
- In Asia, susceptibility to tear duct obstruction may increase because of air pollution, particularly in highly populated areas with dense urban living. Preventive medicine and routine examinations are therefore frequently emphasized.
- In rural parts of Anatolia and similar agricultural communities, watery eyes may be attributed to "dust" and neglected for extended periods. This may cause the condition to become chronic and progress until surgery is required.
These examples demonstrate that the problem is universal and that the fundamental treatment approaches are similar, although minor differences may occur in practice.
- Maintain Proper Hygiene
Keeping the area around the eyes clean and preventing the accumulation of discharge reduce secondary infections. Be gentle when wiping the eye with disposable tissues or clean cotton cloths.
- Use Prescribed Drops and Ointments Regularly
Drops containing antibiotics, corticosteroids, or other active ingredients should always be used exactly as prescribed. Because of the anatomy of the eye, correct application technique, such as gently pulling down the lower eyelid, is also important.
- Learn the Massage Technique, Particularly for Babies
Massage performed by applying pressure over the lacrimal sac as demonstrated by the doctor is a simple but effective method. Perform the massage at the recommended frequency and according to the recommended routine.
- Avoid Windy and Dusty Environments
Excessive exposure to dust, pollen, or wind increases eye irritation and may worsen existing complaints. Protective glasses may be used.
- Keep Makeup Products Clean
Products such as mascara and eyeliner may allow microorganisms to multiply. Check their expiration dates and do not share them with other people.
- Attend Regular Medical Follow-Up Appointments