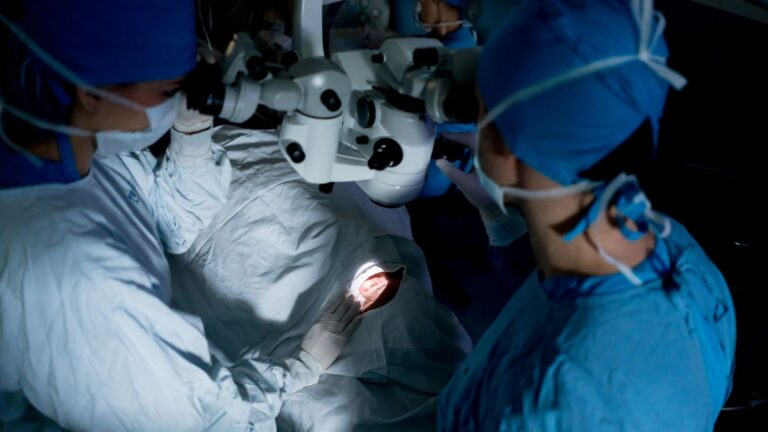
Tear duct obstruction surgery is performed to redirect tears into the nasal cavity. The DSR method provides a permanent solution by creating a new passage that bypasses the blocked duct.
The operation may be performed under local or general anesthesia. The bone between the nose and the eye is thinned, and a new channel is opened. This restores the natural flow of tears.
Watering and infection-related complaints improve considerably after surgery. The procedure has a high success rate and is particularly preferred for chronic obstructions. Recovery is generally short and comfortable.
Regular postoperative follow-up and antibiotic eye drops reduce the risk of infection. DSR is currently one of the most reliable treatment options for tear duct obstruction.
| Definition | A surgical procedure performed when a blocked tear duct prevents tears from draining properly into the nose. It is used to resolve persistent watering, discharge, and infection. |
|---|---|
| Types of Surgery |
Dacryocystorhinostomy, DSR: A new tear drainage pathway is created.
Endoscopic DSR: A closed procedure performed through the nose.
External DSR: Performed through a small incision between the eye and the nose.
Balloon Dacryoplasty: A balloon is used to widen mild obstructions.
| Who Is It Performed For? | Patients with chronic tear duct obstruction, recurrent eye infections known as dacryocystitis, or no response to medication or other treatments. |
|---|---|
| Duration of Surgery | Approximately 30 to 60 minutes. It may be shorter with the endoscopic method. |
| Type of Anesthesia | Generally performed under local anesthesia, although general anesthesia may be preferred in some cases. |
| Recovery | Patients are generally discharged on the same day. Normal activities may be resumed within 1 to 2 weeks. Complete recovery may take several weeks. |
| Potential Risks and Complications | Mild bleeding, nasal congestion, infection, and mild eye discomfort. In rare cases, the passage may become blocked again. |
| Postoperative Care | Antibiotic eye drops prescribed by the doctor should be used. Rubbing the eye, strenuous exercise, and blowing the nose should be avoided. |
| Success Rate | Has a high success rate ranging from 85% to 95%. |
Tear duct obstruction surgery is a surgical procedure performed to open blocked tear drainage pathways. DSR, dacryocystorhinostomy, is one of the most common methods and aims to bypass the obstruction so that tears can drain into the nasal cavity. The procedure is generally performed for patients with watering, infection, and discharge. It may be performed under local or general anesthesia and has a high success rate.
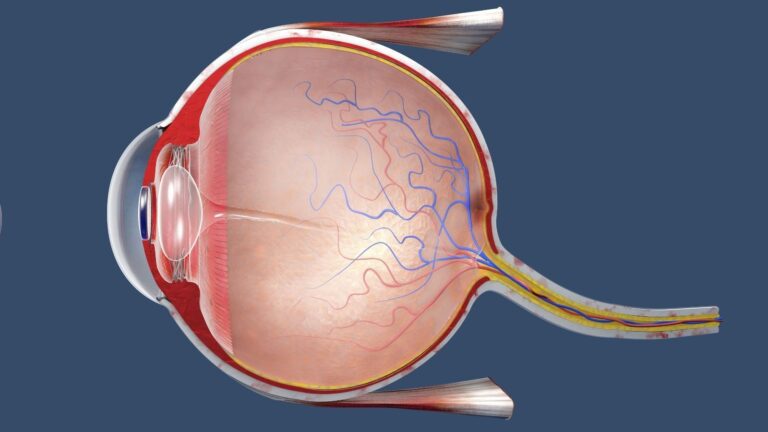
The basic principle of DSR surgery is to create a new pathway, much like bypassing a blocked water pipe. The surgeon creates a direct connection between the lacrimal sac and the nasal cavity. This new pathway allows tears to flow into the nose through the newly created "passage" instead of the old blocked duct.
- Identifying the Obstruction: The location of the blockage is determined first. This may be done using colored liquids introduced into the tear ducts, endoscopic examinations, or radiological imaging such as CT scans.
- Creating a New Passage: During surgery, the surgeon creates a direct opening between the lacrimal sac and the nasal cavity. A thin silicone tube, stent, may sometimes be inserted and left in place for a period to prevent the new passage from closing after surgery.
- Recovery Period: Regular examinations are performed during the weeks following surgery to ensure that the new passage becomes established without adhering or becoming blocked again. If a stent has been inserted, it is removed at the end of the healing period.
Following surgery, tears flow into the nose through the "newly created pathway" rather than overflowing because the "original pathway" is blocked. Persistent watering, epiphora, discharge, and recurrent infections are therefore largely resolved.
Some people are born with narrow or blocked tear ducts. In others, the problem develops later because of trauma, infection, or age-related tissue changes. The principal groups who may require DSR surgery include:
- People With Chronic Epiphora, Excessive Watering: If tears constantly flow down the cheeks and make daily life difficult, there is a high probability of tear duct obstruction. Tears flowing while speaking in a crowded environment may even cause others to misunderstand the situation and ask, "Are you upset?"
- People With Recurrent Eye Infections: Fluid accumulating in the lacrimal sac may become a suitable environment for microbes that trigger infection. People with chronic dacryocystitis, inflammation of the lacrimal sac, frequently experience episodes of swelling, redness, and pain around the eye. Antibiotics or eye drops may provide temporary relief, but DSR surgery is generally the definitive solution.
- People With Sinus or Nasal Problems: Chronic sinusitis, nasal polyps, or previous nasal surgery may cause an obstruction where the tear ducts open into the nasal cavity. As a result, tears that should normally drain into the nose begin to flow outward.
- People With Facial Trauma or Fractures: Serious trauma caused by traffic accidents or falls may affect the bones around the eye. Damage to the bony channels through which the tear duct passes may result in permanent obstruction. DSR surgery may become the only solution in such cases.
- Age-Related Tissue Changes: Advancing age causes changes in tissue elasticity and anatomical structures throughout the body. Natural changes in the tissues around the nose may also cause narrowing or obstruction of the tear drainage pathways.
- Congenital Obstructions: Some babies are born before the tear duct has developed completely. Many cases resolve with massage or simple interventions, while persistent cases may require DSR surgery later in life.
The common feature among these patients is that the normal tear drainage pathway has been blocked in some way, causing problems such as watering or inflammation. DSR is the principal method that provides a permanent solution to this problem.
The most obvious symptom of tear duct obstruction is persistent and excessive watering. Some patients have to carry tissues constantly or report irritation from repeatedly wiping their eyes. Signs that may indicate this problem include:
- Persistent Tearing, Epiphora: Tears may continue to flow in windy weather, while resting at home, or even while watching television. This can be compared to a tap that has been left slightly open.
- Redness and Irritation Around the Eye: Tears are normally protective, but overflowing tears may irritate the eyelid margins. People with sensitive skin may also develop redness and mild rashes.
- Recurrent Inflammation or Infection: Tears accumulating in the blocked area create an ideal environment for microbes to multiply. Swelling and pain near the inner corner of the eye and sometimes yellow-green discharge may develop.
- Crusting or Discharge on the Eyelids in the Morning: Inflammatory fluid leaking from the eye may accumulate and dry on the eyelids overnight. The eyelashes may be stuck together upon waking.
- Pressure and Fullness in the Eye: Some patients experience discomfort as though there is "fullness" near the inner corner of the eye. When the area is pressed gently, fluid may move toward the eyelid or flow outward instead of draining into the nose.
If these symptoms have persisted for a long time and do not improve with methods such as eye drops, medication, or massage, tear duct obstruction becomes a serious possibility. A detailed examination and imaging are then used to determine the source of the problem. DSR surgery may ultimately provide a permanent solution.
Imagine an old, blocked water pipe in your garden. When you turn on the tap, the water flows into the garden or even toward the house instead of reaching its intended destination. Tear duct obstruction is very similar. Just as you would call a plumber to repair the blocked pipe or create a new channel, ophthalmologists use DSR surgery to bypass the blocked tear duct.
Before discussing the technical details, two principal approaches should be mentioned: the external approach and the endoscopic approach.
External DSR
- Location of the Incision: A small incision is made beside the nose in the area where the lacrimal sac is located. It is generally positioned along the skin line near the bridge of the nose, immediately beside the inner corner of the eye.
- Stages of the Procedure: The surgeon exposes the lacrimal sac and surrounding area and clears the blocked points. A direct opening is then created between the lacrimal sac and the nasal mucosa. This connection forms a new passage that assumes the function of the old blocked duct.
- Sutures and Stents: A silicone tube may be inserted during surgery to keep the passage open. Sutures placed in the skin are generally removed within several weeks, and the scar becomes less noticeable over time.
Endoscopic DSR
- No External Incision: The principal advantage is that no visible incision is made between the eye and the nose. The surgeon reaches the lacrimal sac using endoscopic instruments inserted through the nose.
- Use of a Camera and Instruments: Tissues inside the nose are displayed on a screen through the endoscope. After reaching the blocked area, the surgeon removes the obstruction and connects the lacrimal sac to the nasal mucosa.
- Stent Placement: As with the external method, a silicone stent may sometimes be inserted and left inside the nose or tear duct for a period after surgery.
Both methods have the same objective: to eliminate the obstruction and create a new pathway for tear drainage. The choice may vary depending on the patient's anatomy and age, the location of the blockage, and the surgeon's experience. Additional methods such as balloon catheter dilation may be used in some cases. Congenital cases may require only simple probing, in which the duct is opened using a specialized instrument.
The most important benefit of DSR is that it provides a definitive solution to persistent watering and largely prevents related infections. Other potential benefits include:
- Improved Daily Comfort: Eliminating the constant need to wipe the eyes provides significant relief in social settings and professional life. Problems such as skin irritation and redness around the eyes also decrease over time.
- Reduced Risk of Infection: Tears accumulating in the blocked duct provide a suitable environment for bacterial growth. Because drainage returns to normal after surgery, inflammation and abscess formation around the eye decrease considerably.
- Permanent Solution With a High Success Rate: Various studies have shown that DSR surgery has success rates of up to approximately 90%. The success rate may be even higher when postoperative care is performed properly and follow-up examinations are not neglected.
- Improved Quality of Life: Tears flowing down the face may cause stress in many situations, from working life to social environments. The "dry and comfortable" eye achieved after surgery may also have a positive effect on self-confidence.
- Cosmetic Advantage of the Endoscopic Method: Because endoscopic surgery is performed through the nose without leaving a visible external incision, it provides a more cosmetically comfortable recovery. This may be particularly important to some patients.
- Long-Term Solution in Pediatric Cases: If simple massage or probing during infancy does not resolve a congenital obstruction, DSR offers an effective next step. It prevents recurrent inflammation and watering later in the child's life.
As with any surgery, DSR has certain risks. However, appropriate patient selection and an experienced surgeon considerably minimize these risks.
No surgical procedure is completely free of risk. Potential complications of DSR surgery include:
- Bleeding: Mild bleeding may occur during or after surgery. It can generally be controlled and does not cause a serious problem. However, blood may accumulate inside the nose, or a hematoma may develop in the surgical area, particularly during the first few days.
- Infection: Infection may develop around the sutures or in the tissues inside the nose. Redness, pain, or discharge around the eye may be an early sign of infection. With appropriate hygiene and antibiotic support, this risk is generally low.
- Scarring and Adhesions: The new passage between the lacrimal sac and the nasal mucosa may sometimes close or narrow during healing. This may cause recurrent obstruction. Because nasal tissues have a strong tendency to heal, postoperative examinations and keeping the stent in place when necessary are important.
- Problems Related to the Silicone Tube, Stent: The tube may become displaced, cause irritation, or create discomfort. This generally occurs during the early postoperative period and can be resolved with corrective intervention.
- General Anesthesia and Other Surgical Risks: Older patients or people with additional conditions may experience anesthesia-related complications or additional difficulties during recovery.
- Damage to Nearby Tissues: Previous surgery or trauma affecting the internal nasal structures or the area around the lacrimal sac may alter the anatomical boundaries and make surgery more complicated. Although rare, there is a risk of damage to neighboring tissues.
The general principle of surgery is to consider the "risk-benefit" balance. When tear duct obstruction causes advanced discomfort and reduces quality of life, the benefits of surgery generally outweigh these risks. Frequent and regular postoperative examinations help identify potential complications at an early stage.
Immediately after surgery, the patient may not experience a situation in which "my eye has stopped watering completely." Recovery progresses gradually, and tear drainage returns to normal during this process. In general:
- First 24 to 48 Hours: Mild aching, swelling, and even bruising around the eye are normal during this period. Slightly bloodstained discharge may come from the nose or surgical area. Pink-colored tears are also not a cause for alarm.
- First Week: Swelling gradually decreases. If the operation was performed through an external incision, mild firmness or crusting may appear around the sutures.
- Day 10 and Beyond: Most patients can return to their daily activities. If a stent has been inserted, a small tube may be felt inside the nose or near the inner corner of the eye. The tube generally remains in place for approximately 6 to 12 weeks.
- First Month: Most swelling has resolved, and the frequency of watering has decreased considerably. Every patient's recovery rate may naturally differ.
- Third Month and Later: Any scar or thickened tissue in the surgical area gradually becomes less noticeable. Tear drainage becomes more stable. If a stent is present, it may be removed during this period when considered appropriate.
Questions such as "Can I wear makeup?" and "Can I exercise?" are frequently asked after tear duct surgery. It is generally advisable to avoid strenuous exercise, activities requiring bending, and applications that may irritate the eye area for approximately one week. However, these periods may vary according to the patient and the surgical method.
When surgery is planned, patients generally begin to wonder, "What should I expect?" The following steps and situations may arise before and after the operation:
Before Surgery
- Examination and Imaging: To establish a definitive diagnosis, the doctor may perform tear duct tests using drops, insert a thin probe into the duct to measure the level of the obstruction, or use radiological methods such as CT and dacryocystography to visualize the problem.
- Medication Adjustments: If the patient takes medications such as blood thinners, they may sometimes be asked to discontinue them for a period before surgery. It is important to disclose all existing conditions and medications at this stage.
- Assessment of General Health: Some patients undergo surgery under local anesthesia, while general anesthesia may be preferred for others. Age, additional medical conditions, and personal comfort are important considerations.
After Surgery
- Mild Pain and Edema: Mild pain, swelling, and slight bruising may occur around the bridge of the nose and eye during the first few days. This is a natural result of the procedure and can generally be controlled with cold compresses or prescribed pain medication.
- Nosebleed or Bloodstained Tears: Because a new passage has been created, tears may be mixed with blood for a short time. Mild leakage from the nose is also considered normal.
- Suture Care in External DSR: Attention should be paid to suture hygiene. The surgeon provides instructions about dressing and cleaning, although gentle cleaning is generally sufficient.
- Examinations and Suture Removal: Follow-up appointments are arranged during the first week or 10 days after surgery. If the sutures need to be removed, they are removed during this period. If a stent has been inserted, instructions are provided regarding its care.
- Long-Term Relief: After the mild discomfort of the first few weeks has passed, watering decreases considerably, and episodes of infection become much less frequent.
During this period, it is important to avoid rubbing or applying pressure to the eyes and to avoid forceful movements while cleaning the nose. Gentle walks while resting at home may improve circulation and support recovery.
Congenital tear duct obstruction generally becomes noticeable during the first months of a baby's life. Persistent watering and discharge may concern parents. Fortunately, tear duct obstructions in most babies can be opened with massage or a simple probing procedure. In some persistent cases, however, DSR surgery may be considered when the child is older.
- Simple Cases: Most congenital obstructions develop because of a thin membrane, the membrane of Hasner, at the lower end of the tear duct. This membrane often opens spontaneously or with massage, resolving the problem.
- Persistent Obstructions: If the membrane does not open or additional narrowing is present in the duct, probing may be performed. If this is unsuccessful or the child becomes older and begins to experience frequent inflammation, DSR offers a permanent solution.
- DSR in Children: Surgical approaches in congenital cases may differ slightly from those used in adults, but the objective remains the same: to create a new pathway through which tears can drain into the nose. When performed at the appropriate time using the correct technique, surgery prevents children from experiencing problems such as infections or persistent watering later in life.
In conclusion, DSR is also highly effective for congenital obstructions. The important point is to monitor the child's condition closely and determine at the appropriate time whether surgery is genuinely necessary.
Before undergoing surgery, most people naturally wonder, "What do I need to do?" Preparation for tear duct obstruction surgery, DSR, generally consists of the following steps:
Medical Assessment:
- Current medications, particularly blood thinners, and supplements, including certain herbal products, are reviewed.
- If chronic conditions such as hypertension, diabetes, or heart disease are present, recent medical tests related to these conditions are performed.
Imaging Methods:
- The doctor may request a CT scan or imaging tests using special contrast dyes to examine the tear drainage pathways in detail.
- A decision is made regarding whether the surgery will be performed using an external or endoscopic method.
Diet and Rest:
- If general anesthesia will be used, eating and drinking may be prohibited after a specified time on the night before surgery. Although this procedure can sometimes be performed under local anesthesia, mild sedation or general anesthesia may generally be preferred.
- Avoiding alcohol during the days before surgery helps support the immune system.
Comfortable Clothing and Personal Care:
- Makeup, eyeliner, mascara, and similar products should not be used on the day of surgery. This reduces the risk of infection and makes the surgeon's work easier.
- Hairbands, hair clips, jewelry, and similar accessories should be kept to a minimum because they may cause problems in the operating room.
Companion and Comfort Arrangements:
- The area around the eye may be bandaged or slightly swollen after surgery. Having someone accompany the patient is helpful for spending the first day at home comfortably and safely managing potential problems.
- The bed or resting area at home may be prepared to be as clean and comfortable as possible. Keeping the head elevated for a period with additional pillows may help reduce edema.
Emotional and Psychological Preparation:
- Surgical procedures may always cause some anxiety. Understanding the operation and having the doctor explain "how" and "why" it is performed may help reassure the patient.
- It is important not to become overwhelmed by negative thoughts about surgery. Tear duct surgery is now a frequently performed procedure with well-understood technical details and is successfully carried out by specialists.