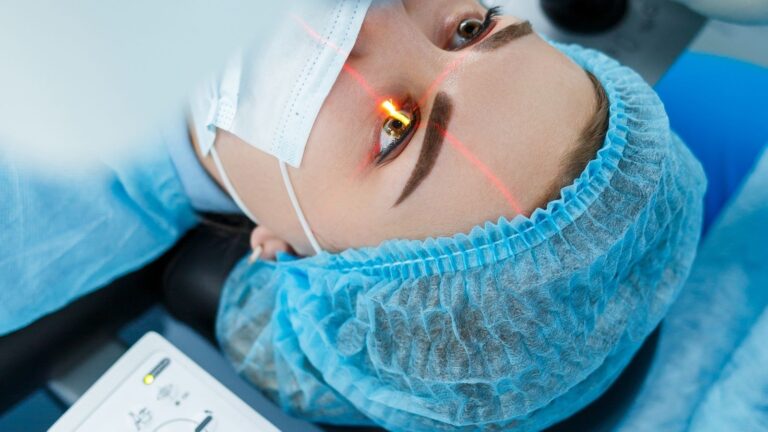
Corneal cross-linking is a modern treatment used to strengthen the cornea in keratoconus. Riboflavin drops and a special light are used to strengthen the bonds between collagen fibers in the cornea. This procedure slows vision loss.
During the first few days after treatment, stinging, burning, and blurred vision may occur. These symptoms are temporary and usually improve within a few days. With appropriate eye drop treatment and medical follow-up, healing progresses rapidly and the cornea becomes stable.
Corneal cross-linking reduces the need for corneal transplantation by stopping the progression of the disease. This method produces particularly effective results in keratoconus patients diagnosed at a young age. The success rate increases when treatment is performed at an early stage.
In the long term, strengthening the corneal structure may improve visual quality. However, the procedure does not always provide complete correction. Its primary aim is to slow disease progression. Regular follow-up and additional treatment methods play an important role in managing the disease.
| Definition | Strengthening the corneal tissue using riboflavin (vitamin B2) drops and UV-A light |
|---|---|
| Areas of Use | Keratoconus, corneal ectasia, and certain progressive conditions that weaken the cornea |
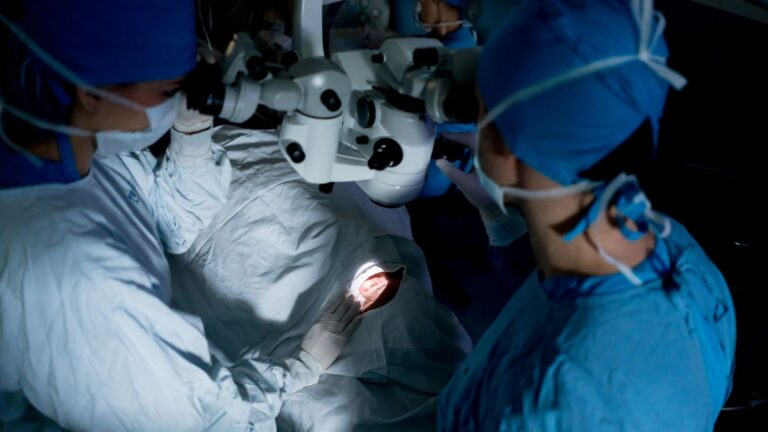
| Method of Application | Removal of the corneal surface after local anesthetic drops, application of riboflavin drops, followed by exposure to UV-A light (approximately 30-60 minutes) |
| Preparation | Special preparation is generally not required. Depending on the doctor's recommendation, contact lenses should not be worn on the day of the procedure |
| Side Effects | Temporary stinging, pain, light sensitivity, temporary corneal haze, and, rarely, infection or ulceration |
| Advantages | May stop or slow the progression of keratoconus and may eliminate the need for surgery |
| Disadvantages | Temporary blurred vision, a recovery period that may last several weeks, and a rare risk of infection |
| Who Should Not Undergo It | People with thin corneas (thinner than 400 microns), an active eye infection, or a severe corneal ulcer |
| Who Undergoes It More Frequently | Young patients with progressive keratoconus and those diagnosed at an early stage |
| Recovery Time | Return to daily life generally within 1-4 weeks. Final vision may stabilize within 2-6 months |
| Complications | Temporary corneal haze, infection, ulceration, and vision loss (very rare) |
| When to Consult a Doctor | If severe pain, sudden reduction in vision, discharge, redness, or light sensitivity develops |
Corneal cross-linking is a treatment used to increase the structural strength of the cornea in progressive corneal diseases such as keratoconus. After riboflavin (vitamin B2) drops are applied to the cornea, UV-A light is used to create new bonds between collagen fibers. This makes the cornea stronger and more stable. It does not improve vision, but aims to stop the progression of the disease.
Corneal cross-linking is recommended particularly in cases where corneal ectasia, such as keratoconus or post-LASIK ectasia, is progressing. How is this progression detected? Parameters such as a rapid increase in the patient's glasses or contact lens prescription and trends toward corneal thinning and steepening on corneal topography are monitored. An increase of more than 1 diopter in the steepest corneal curvature (Kmax) over a one-year period or a significant change in the prescription may generally be interpreted as a sign of "progression." The greatest concern with keratoconus is that it can progress rapidly at a young age and seriously threaten visual quality.
- Age Factor: Most studies show that corneal cross-linking may be more effective at younger ages. This is because keratoconus can progress rapidly, particularly during adolescence and the early twenties. The natural course of keratoconus may slow relatively during the thirties and forties. Nevertheless, treatment may also be applied to adults whose condition is progressing.
- Corneal Thickness: One of the most critical requirements for the procedure is generally a corneal thickness of at least 400 microns. UV-A light can damage the corneal endothelium, which is the innermost layer of the cornea. If the cornea is too thin, the light may reach the endothelium and cause irreversible damage. Various modifications have been developed for thin corneas, such as hypo-osmolar riboflavin or contact lens-assisted techniques, but these are also applied only under specific conditions.
- Corneal Transparency and Scarring: During the procedure, the riboflavin drops must penetrate the corneal stroma effectively. Penetration of the medication and light may be difficult in a severely scarred or cloudy cornea. Therefore, results may not be as favorable as expected in patients with severe scar tissue.
- Autoimmune Diseases: Immune system disorders may negatively affect tissue healing. Some doctors recommend a careful assessment before CXL in people with connective tissue diseases such as rheumatoid arthritis. The regenerative ability of ocular tissue may differ in these patients, and the risks of infection or inflammation may be higher.
- History of Herpetic Eye Disease: In patients who have previously had a herpes infection of the eye, such as herpes keratitis, the virus may remain dormant. The corneal cross-linking procedure or medications used afterward may reactivate the virus. For this reason, treatment is generally not recommended for these patients, or very strict precautions are taken.
In addition to all these criteria, the final decision regarding corneal cross-linking is based on the patient's overall clinical condition and the ophthalmologist's experience. The aim is to intervene as early as possible in patients who have the highest likelihood of progression and prevent permanent vision loss.
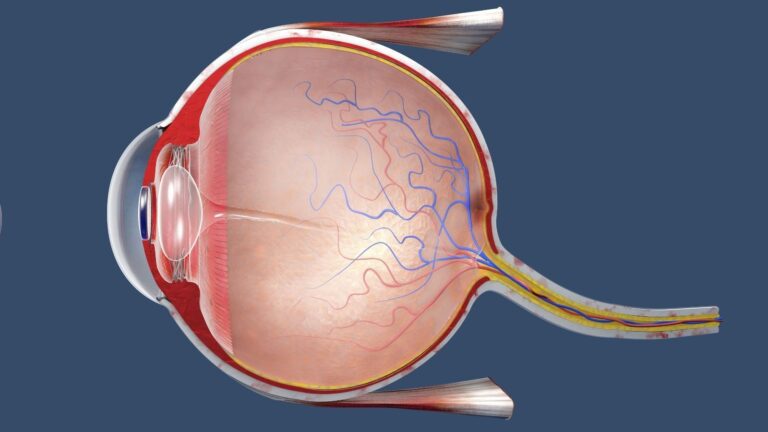
The basic principle of this procedure is that riboflavin (vitamin B2) and UV-A light initiate a chemical reaction. Riboflavin accumulates in the corneal stroma and becomes sensitive to light. When UV-A light with a wavelength of approximately 365-370 nm is then applied, chemicals known as "reactive oxygen species" are produced. These reactive oxygen species create additional bonds, known as cross-links, between collagen fibers and cause the tissue to become stronger.
This process can be compared to placing additional steel bars between the columns of a building to increase the strength of the concrete. The stronger the connections between the columns, the more resistant the building becomes to external forces. Similarly, increasing the number of cross-links within the cornea helps the tissue become more resistant to external forces and intraocular pressure.
- Important Point: Corneal cross-linking strengthens the existing tissue structure. It does not thicken areas that have been lost or severely thinned in the sense of "treating" them. Therefore, corneal transplantation may be required in advanced cases. However, CXL can often be considered a preventive measure taken before the disease reaches this stage.
- Role of the Epithelium: The cornea is covered by a layer of cells called the epithelium. This layer protects the eye from the external environment but may partially prevent riboflavin absorption. In the conventional epi-off method, the epithelium is removed so that riboflavin can easily penetrate the corneal stroma and the procedure can be performed more effectively. However, removing the epithelium reduces patient comfort after the procedure and slightly increases the risk of infection. For this reason, methods in which the epithelium is not removed (epi-on) or is made partially permeable have recently been developed.
- Cell Protection: If the cornea is sufficiently thick, UV-A light exerts its effect at the stromal level without threatening the endothelium, the innermost layer of the cornea, or the ocular tissues behind it. This is why measuring corneal thickness before the procedure is very important.
To ensure that this mechanism functions correctly, the light intensity, application time, and riboflavin concentration are adjusted very precisely during the procedure. This allows the desired biochemical effect to occur while protecting the other layers of the eye.
Corneal cross-linking is primarily divided into two main methods: epithelium removal (epi-off) and epithelium preservation (epi-on). Accelerated protocols, also known as A-CXL, and various modifications have also gained popularity in recent years.
Epithelium-Off (Epi-Off) Method
- This is the most conventional protocol and has the strongest supporting evidence.
- Local anesthesia is first applied to the eye surface in the form of drops.
- The central 8-10 mm section of the corneal epithelium is carefully removed.
A 0.1% riboflavin solution is then applied for approximately 30 minutes, generally every 2-5 minutes, to saturate the corneal stroma with the solution.
After the cornea has been sufficiently saturated with riboflavin, UV-A light with a wavelength of 365-370 nm is applied to the corneal surface for a specified period, generally 30 minutes, at a specific intensity of 3 mW/cm².
The total energy dose is adjusted to 5.4 J/cm².
- At the end of the procedure, a protective bandage contact lens is placed on the corneal surface, and the patient is given antibiotic and steroid eye drops. Regrowth of the epithelium generally takes several days.
Epithelium-On (Epi-On) Method
- The corneal epithelium is not removed. As a result, the patient's comfort after the procedure is relatively better, and the risk of infection is relatively lower.
- However, because the epithelium partially prevents riboflavin from penetrating the cornea, the amount of cross-linking achieved may be lower than with the epi-off method.
- Some protocols attempt to increase riboflavin penetration using special solutions or technologies such as iontophoresis. Nevertheless, many studies show that the standard epi-off protocol provides more consistent and stronger results.
Accelerated Protocols
- The aim is to shorten the treatment time by increasing the light intensity without changing the total energy dose of 5.4 J/cm². For example, instead of applying 3 mW/cm² for 30 minutes, 9 mW/cm² may be applied for approximately 10 minutes.
- This approach aims to shorten the procedure while maintaining a similar level of effectiveness. However, some studies suggest that short applications at very high intensity may have a more superficial effect on the cornea.
Pulsed Light Application
- UV-A light is applied intermittently rather than continuously. This allows oxygen within the corneal tissue time to replenish and may make the cross-linking reactions more effective.
- Although various studies have found no significant difference between pulsed and continuous light protocols, it is thought that periodically replenishing oxygen may improve the quality of the procedure in some cases.
Customized (Topography-Guided) Cross-Linking
- Developing technologies allow targeted UV-A application to the weakest areas of the cornea or planning based on the patient's individual topography.
- This approach aims to provide more selective treatment by concentrating on the weaker areas of the cornea. However, these applications are still in the research and development stage.
Special Techniques for Thin Corneas
- Because the risk of endothelial damage increases in corneas thinner than 400 microns, methods such as hypo-osmolar riboflavin or contact lens-assisted CXL may be preferred.
- In the contact lens-assisted method, a special contact lens saturated with riboflavin is placed on the eye. The combined thickness of the cornea and lens provides safe exposure to UV light.
Each method has advantages and disadvantages. Factors such as the patient's ocular structure, corneal thickness, and rate of disease progression play a determining role in selecting the protocol. However, the greatest amount of data and evidence is available for the epi-off method known as the conventional Dresden protocol. Doctors generally use this protocol as a basis and make modifications for specific circumstances when necessary.
After corneal cross-linking, patients can expect a recovery process lasting from the first postoperative days to several months. The changes and symptoms experienced during this period can be examined under several headings:
First Few Days: Pain, Burning, and Light Sensitivity
- Because the corneal epithelium is removed during the epi-off method, significant eye pain, burning, and stinging may occur during the first 24-48 hours after the procedure. This period can be compared to a situation in which the skin has been scraped.
Sensitivity to light increases in particular, and watering and redness of the eyes may be observed.
- The bandage contact lens given to the patient both protects the cornea and reduces pain. Antibiotic drops minimize the risk of infection, while steroid or similar anti-inflammatory drops support healing.
First Week: Regrowth of the Epithelium and Visual Fluctuation
- The removed epithelial layer generally regrows within 3-5 days. During this period, the patient attends follow-up appointments at the frequency recommended by the doctor, and a decision is made regarding the removal of the bandage lens.
- Blurred vision or halos around lights may occur. This is associated with postoperative corneal swelling, tissue regeneration, and surface irregularity.
First Months: Fluctuations in Visual Clarity and Recovery
- After several weeks, vision gradually becomes more stable, but achieving fully stable and clear vision may take several months.
- During this period, corneal topography measurements may show gradual improvement or at least stabilization. Some patients may report seeing "better than before," but the primary objective is to stop keratoconus from progressing further.
- Short-term fluctuations in visual clarity, such as clear vision in the morning followed by mild deterioration toward the evening, are considered normal.
Long Term: Stabilization and Possible Improvement
- Although cross-links within the cornea begin to form immediately after the procedure, complete tissue remodeling and achievement of maximum strength may take 6-12 months.
- Studies show that after one year, many patients experience some improvement in maximum keratometry readings (Kmax) and permanent improvement or stabilization of visual acuity.
- Clinical studies have observed that keratoconus does not progress in the vast majority of treated eyes. Some patients have also shown a reduction of approximately 1 diopter in keratometry values.
- Example of Visual Improvement: Some patients need high-prescription contact lenses to see clearly before the procedure. Over time after cross-linking, they may experience a small reduction in this prescription. As a simple example, a corneal curvature measurement of 5.0 diopters may decrease to 4.0-4.5 diopters. Such a pronounced improvement does not occur in every case. However, even stopping progression provides a major advantage in preserving vision.
Some patients may develop mild cloudiness known as corneal haze after the procedure. In most cases, this haze is temporary and decreases within 3-4 months. Prolonged or permanent haze is rare and generally causes only a minimal reduction in visual quality that can be corrected with glasses or contact lenses.
With increasing experience and technological developments, corneal cross-linking is now considered a highly safe procedure. However, as with every medical procedure, CXL has certain risks and side effects.
Temporary Side Effects
- Stinging and Burning: These may be particularly noticeable during the first few days when the epi-off technique is used.
- Light Sensitivity: The eyes may become less tolerant of bright light. Wearing sunglasses can provide relief.
- Dry Eye: A temporary deterioration in tear quality may occur and can be managed with artificial tear drops.
- Blurred or Hazy Vision: Fluctuations in vision and mild blurriness are normal, particularly during the first few weeks.
More Serious but Rare Complications
- Corneal Infection: In procedures performed without the epithelium (epi-off), the ocular surface may become more exposed to microorganisms. Regular use of prescribed postoperative antibiotic drops is therefore important.
- Prolonged Corneal Haze: Although it generally decreases within several months, it may rarely become more permanent and affect visual quality.
- Corneal Scarring: Scar tissue may form in the cornea due to an excessive reaction or infection. Early diagnosis and treatment are important because this may cause permanent visual impairment.
- Endothelial Damage: If the cornea is too thin or the UV dose is not adjusted correctly, the endothelium, the innermost layer of the cornea, may be damaged. If the balance of fluid within the eye is disrupted, this may result in corneal swelling and severe vision loss.
Positive Statistics
- In one study, 117 eyes were monitored for 12 months, and the complication rate was reported as 2.9%. This rate is quite low compared with many surgical procedures.
- In the same study, a "failure" rate of 7.6%, meaning that progression could not be stopped, was reported. Although this figure may initially appear high, it should be remembered that more than 90% of patients benefited from the treatment.
- Long-term follow-ups covering periods of 5-7 years have also shown that serious complications are uncommon.
Risk Factors:
- Patients with very thin corneas,
- Keratoconus cases with a very high Kmax value (above 58 diopters),
- Keratoconus that progresses rapidly at a young age,
- Systemic or local immune system problems,
- Patients who do not follow hygiene rules or miss their follow-up appointments,
are at a slightly higher risk of complications. However, these risks can be significantly reduced through thorough preparation, meticulous performance of the procedure, and regular follow-up.
In conclusion, corneal cross-linking is considered a relatively safe procedure. The quality of the equipment, the experience of the doctor, and the patient's adherence to postoperative care instructions are the most important factors determining success.
When the procedure was first introduced, some researchers described it as "revolutionary." Previously, no effective treatment was available to stop the progression of keratoconus. What statistics do we have today, and what can patients expect from this treatment in the long term?
Stopping the Progression of Keratoconus
- Numerous clinical studies show that corneal cross-linking significantly slows or completely stops the progression of keratoconus.
- A study published in the Journal of Cataract & Refractive Surgery reported flattening at the steepest point of the cornea in 70% of patients and improved visual acuity in 65%. This is an indication of genuine structural improvement in the cornea.
- In another follow-up study, no significant progression of keratoconus was detected in treated eyes during a seven-year observation period. Progression was recorded in the control group during the same period. These findings indicate that the treatment may also be effective in the long term.
Improvement in Visual Acuity
- Although the primary purpose of corneal cross-linking is to stop progression, it may also provide a meaningful improvement in visual quality in some cases.
- A meta-analysis identified an average reduction of approximately 1 diopter in Kmax after the procedure and reported a clear improvement in visual acuity of up to 65% in some patients during the following months.
- More pronounced improvements may be observed after treatment, particularly in patients with very high preoperative diopter values or low visual acuity.
Retreatment (Repeated Procedures)
- In some patients, keratoconus may begin to progress again several years after the first procedure.
- In another study presenting 15-year follow-up data, 14% of patients required a repeat procedure after an average of nine years. Although this rate is not high, it demonstrates the importance of long-term follow-up.
Cost-Effectiveness Analysis
- Because corneal cross-linking can often prevent the need for a more invasive and costly procedure such as corneal transplantation, it has been found advantageous in the long term in terms of both patient comfort and healthcare economics.
- A cost-effectiveness study showed that although the initial cost of CXL may appear high, it prevents permanent vision loss and reduces potential future surgical expenses. Because it also significantly preserves the patient's quality of life, this method has started to be included in reimbursement programs in many countries.
Pediatric Patients
- Because keratoconus is known to follow a more aggressive course at younger ages, CXL is particularly important in children and adolescents.
- Studies with more than 10 years of follow-up have reported that CXL performed at an early stage in children both preserves vision and significantly slows the progression of keratoconus.