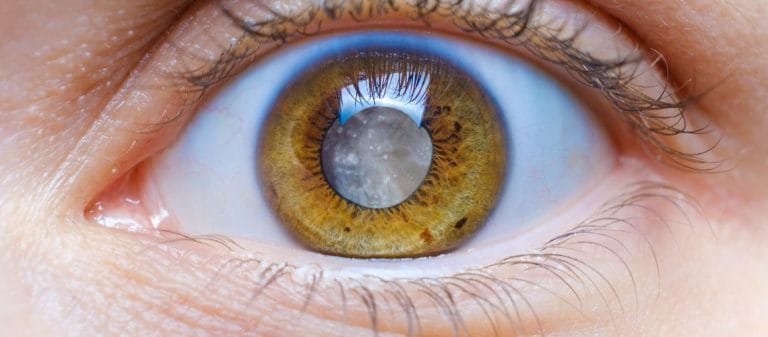
The artificial lens implanted inside the eye after cataract surgery generally remains stable for life. However, in rare cases, lens displacement may occur because of capsular weakness or trauma, potentially resulting in reduced visual quality.
Symptoms of lens displacement include blurred vision, double vision, halos around lights, and reduced visual acuity. Early intervention is important when these complaints develop.
Risk factors include weak ocular structures, trauma, certain eye diseases, and postoperative complications. Regular examinations allow displacement to be detected early.
Treatment varies according to the position of the lens. Glasses may be sufficient for mild displacement, while surgical revision may be required in advanced cases. Medical follow-up plays a critical role in protecting vision.
Postoperative "lens displacement" refers to movement of the artificial lens from the capsule or lens bed in which it was implanted into an unintended position. This movement may remain at the level of a minor decentration, meaning a slight shift from the center, or progress to dislocation, meaning complete displacement. Just as a poorly secured vase may wobble, even a small angular deviation of the lens can cause noticeable problems with visual quality. In more advanced cases, the implanted lens may move completely into another part of the eye.
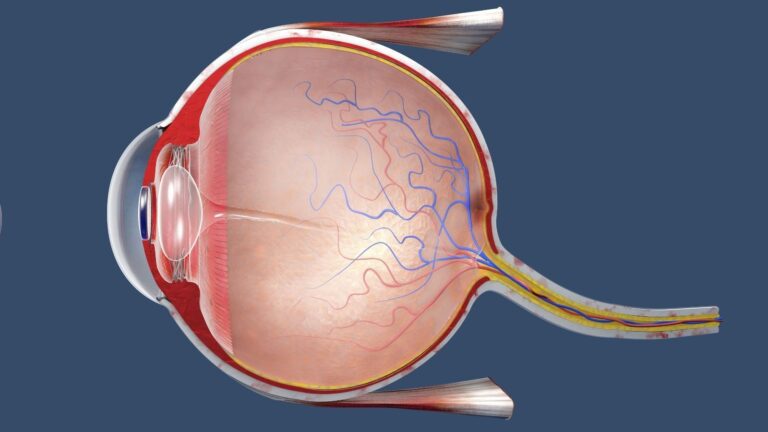
Lens displacement may be triggered by many factors, ranging from intraocular pressure and minor trauma during surgery to the patient's age and ocular structure. Zonular weakness, which may remain clinically undetected like a hidden tear beneath a carpet, can prevent the lens from remaining stable and result in displacement years later. The zonules are the fine supporting fibers surrounding the lens. Long-term observation and follow-up after cataract surgery are therefore important.
- Zonular Weakness or Damage
The fine fibers that anatomically secure the eye's natural lens are known as the zonules. Like a chandelier hanging in the center of a ceiling, these fibers surround the lens almost 360 degrees and hold it within the capsule. Pseudoexfoliation (PEX) and connective tissue disorders such as Marfan syndrome and Ehlers-Danlos syndrome can weaken the natural structure of these fibers. Trauma during surgery or later may also damage the zonules. Like a swing that has lost several of its supporting ropes, this imbalance increases the risk of lens displacement.
- Capsular Contraction
After the eye's natural lens has been removed, the remaining lens capsule undergoes healing and fibrosis, meaning the formation of scar tissue. In some patients, the capsule contracts more rapidly and excessively than normal, creating tension that may pull the lens away from the center. Like the crust of freshly baked bread quickly hardening and compressing the inside, this process may alter the position of the intraocular lens over time.
- Trauma
The eye is extremely sensitive to external forces. A blow sustained during the early or late postoperative period may cause substantial changes to the internal structures of the eye. Even an impact or fall that appears minor may move the implanted lens away from its intended position. The physician's recommendations regarding sports and activities that may cause physical trauma should therefore be followed after eye surgery.
- Surgical Technique and IOL Design
Every eye operation is planned using the technique most appropriate for the patient's ocular structure. However, techniques other than standard phacoemulsification or additional materials, such as a capsular tension ring (CTR), may be required to support weak zonules. The material of the artificial intraocular lens and the design of its haptics, the supporting arms that hold it in place, also influence the risk of displacement. Some designs are like a table with narrow legs placed on a slippery floor, where even a small disturbance may disrupt its balance. Other lens types may reduce this risk through thicker edges or a three-piece structure.
- Systemic Diseases and Other Eye Operations
Systemic conditions such as diabetes, hypertension, and rheumatic diseases may negatively affect the repair mechanisms of ocular tissues. Operations involving the posterior segment of the eye, such as pars plana vitrectomy (PPV), may also affect the integrity of the intraocular anatomy. Removal of the vitreous gel, the transparent gel-like substance filling the eyeball, during these procedures may leave the lens support more vulnerable. Like making substantial changes to the supporting columns of a building, this may create conditions that allow the lens to shift over time.
Lens displacement after cataract surgery may sometimes progress for a long time without causing symptoms. Mild decentration may initially be noticed only as slight blurred vision or mild light scatter around lights at night. Displacement at the level of a true dislocation can cause more noticeable and suddenly developing problems. Lens displacement should be considered when the following symptoms occur:
- Reduced and Blurred Vision: Television subtitles that were previously clear with the usual glasses may suddenly become blurred, or reading a book may become difficult. If the lens has shifted, this can occur because its optical axis has changed.
- Monocular Diplopia (Double Vision in One Eye): A tilted lens may cause the same object to be projected into the eye from two different angles. This may produce disturbing double vision similar to overlapping reflections in a mirror.
- Light Sensitivity and Glare (Glare and Halos): Halos around headlights, glare, or increased light scatter while driving at night may be associated with lens decentration.
- Discomfort, Stinging, or Pain in the Eye: An abnormally positioned lens may trigger friction or inflammatory reactions inside the eye. This may be felt as pain, itching, or sometimes watering.
- Seeing the Lens Edge or "Edge Shadows": In some cases, patients may feel as though they can see the edge of the lens when changing their direction of gaze. A dark peripheral shadow may be perceived like light leaking through a poorly fitted doorframe.
- Sudden Vision Loss or a Change in Vision: Severe displacement or complete movement of the lens into the vitreous cavity at the back of the eye may cause sudden and dramatic vision loss.
A comprehensive eye examination is essential for detecting lens displacement early. This examination can be compared to a detailed structural inspection performed to determine whether the supporting columns of a building contain damage or fractures. Several important methods are used:
- Visual Acuity Measurement: Distance and near vision are evaluated to determine the degree of visual impairment caused by lens decentration.
- Biomicroscopy (Slit-Lamp Examination): The anterior segment of the eye, including the cornea, iris, and intraocular lens, is examined in detail under a narrow beam of light. The position and tilt of the lens, integrity of the capsule, possible fibrosis, and zonular damage can be identified.
- Gonioscopy: The anterior chamber angle is examined. The physician investigates whether the lens haptics have shifted forward and whether they are touching the drainage angle of the eye.
- Ultrasound Biomicroscopy (UBM): If the lens has moved toward the posterior parts of the eye and cannot be visualized clearly from the anterior segment, a detailed examination is performed using high-frequency ultrasound. This is particularly effective for detecting zonular damage or abnormalities behind the capsule.
- Anterior Segment OCT (Optical Coherence Tomography): This method complements biomicroscopy and produces a clear cross-sectional image by scanning the cornea, iris, and lens position layer by layer. The angle of the lens, capsular thickness, lens-haptic complex, and other details can be identified.
- Fundus Examination (Dilated Retinal Examination): If posterior dislocation of the lens is suspected, examination of the retina must not be neglected. A lens that falls into the vitreous cavity may place pressure on the retinal surface and even cause a tear or retinal detachment.
Like a slightly crooked picture hanging on a wall, minor decentration may not always cause significant visual impairment. However, if the picture is heavy and at risk of falling, intervention becomes necessary. Similarly, a treatment plan is required when lens displacement causes significant symptoms or threatens vision:
- Observation and Regular Examinations: If the displacement is minimal and does not affect visual quality, follow-up at regular intervals may be sufficient. Intraocular pressure measurements and examination of the back of the eye should not be neglected during this period.
- Surgical Correction or Repositioning: In mild or moderate decentration, the IOL may be surgically repositioned if it can be recentered within the capsule. Capsular tension rings may sometimes be used to reinforce the zonules and help the lens remain stable. When necessary, the lens may be secured to the sclera, the wall of the eye, or the iris with sutures.
- IOL Exchange: If the lens design is unsuitable, the lens is severely deformed, or it has moved into a position where it cannot be repaired, a completely new IOL may need to be implanted. In cases where the lens cannot be supported in the posterior chamber, anterior chamber IOLs or scleral fixation techniques may be used. Like securely bolting down a table that cannot remain stable on a slippery floor, these techniques provide firmer support for the lens.
- Pars Plana Vitrectomy (PPV): If the lens has fallen into the posterior segment or vitreous cavity, or is moving freely within the vitreous, it must be removed or repositioned with PPV. During this procedure, the retina can also be examined and additional problems such as tears, bleeding, or retinal detachment can be treated immediately.
Lens displacement may sometimes cause no problem by itself, but it may also trigger several serious complications. Just as a leaking tap may gradually damage a wall, displacement can affect the balance inside the eye in several ways:
- Retinal Tears and Detachment: When the lens moves backward and shifts within the vitreous, it may create traction on the retinal surface. This may lead to retinal tears or detachment over time. Vision may deteriorate rapidly and urgent surgery may be required.
- Uveitis-Glaucoma-Hyphema (UGH) Syndrome: An abnormally positioned lens may continuously rub against intraocular tissues, simultaneously causing inflammation (uveitis), increased intraocular pressure (glaucoma), and bleeding (hyphema). This condition is known as UGH syndrome and must be taken seriously.
- Corneal Endothelial Damage and Edema: A lens positioned too close to the anterior segment places mechanical stress on the endothelial cells in the innermost layer of the cornea. Cell loss and swelling may develop over time. In advanced cases, the process may progress to the need for a corneal transplant.
- Vitreous Hemorrhage: Intraocular bleeding may occur when the lens falls into the posterior cavity or moves close to blood vessels during surgery. This may occur more frequently in patients with vulnerable underlying conditions such as diabetic retinopathy.
- Increased Intraocular Pressure: An incorrectly positioned lens may obstruct the circulation of aqueous humor within the eye. This increases intraocular pressure and creates a risk of permanent optic nerve damage.
As with every surgical procedure, a 100 percent guarantee is not possible. However, various precautions can be taken to minimize the risks:
- Careful Surgical Planning: A detailed examination of the eye, advance identification of factors such as pseudoexfoliation, zonular weakness, and high myopia, and planning the operation accordingly should form the basis of the approach.
- Correct IOL Selection: Selecting hydrophilic, hydrophobic, or three-piece lenses, choosing haptic designs compatible with capsular stability, and using strategies involving capsular tension rings when necessary reduce the risk of lens displacement.
- Use of Support Materials: If the zonules are weak or the capsular opening is narrowing, additional materials such as capsular tension rings can support and stabilize the lens.
Regular Examinations and Personal Care: In addition to close monitoring during the early postoperative period, an eye examination at least once a year is recommended over the long term. Avoiding physical trauma, using protective glasses, and consulting a physician when abnormal symptoms occur make early detection of potential problems easier.
Control of Possible Systemic Diseases: Systemic diseases such as diabetes and hypertension affect intraocular circulation and tissue repair. Keeping these conditions under control positively supports healing after surgery.
It is important to obtain a specialist opinion whenever any abnormality in the eye or vision is noticed, from the first few days after surgery to many years later. For example:
- Sudden Blurred or Double Vision: This may be the first sign of lens displacement.
- Eye Pain, Redness, and Light Sensitivity: More extensive problems such as infection or UGH syndrome may be involved.
- Fluctuations in Intraocular Pressure: Particularly when glaucoma or severe eye pain is suspected, fundus examination and pressure measurements should be performed as soon as possible.
- Seeing the Edge of the IOL or Feeling Movement Inside the Eye: This is one of the typical signs of lens decentration.
- The eye can be as delicate and complex as the gear mechanism inside a pocket watch. Any unusual symptom should therefore be evaluated without delay.
Cataract surgery is a highly safe procedure because of technological and surgical advances in medicine. Many patients achieve much clearer vision after surgery and experience a considerable improvement in quality of life. However, the rare complication of lens displacement may negatively affect these gains. This condition may be associated with many factors, ranging from zonular damage and trauma to inappropriate IOL selection. It can generally be controlled with early diagnosis and appropriate treatment.
The position of the artificial lens inside the eye is as important as the foundation stone of a building. When this foundation is positioned securely using an appropriate surgical technique and suitable lens, it can perform its function without problems for many years. Nevertheless, even the smallest hidden problem may develop into significant displacement over time. Regular postoperative examinations, awareness of risk factors, and consistent measures to protect eye health are therefore essential for maintaining a successful surgical outcome.
Concerns about lens displacement can generally be addressed through open communication with the physician. In severe cases or when additional risks are present, specialist surgeons plan the approach most appropriate for the eye's anatomical and physiological requirements. Early intervention generally produces more successful results within a shorter period.